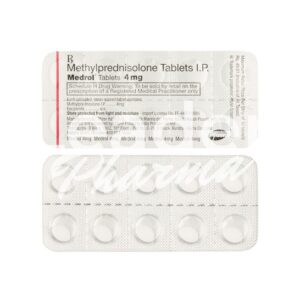
Medrol
In stock
4mg · 8mg · 16mg
from 27,61 £
In brief
Methylprednisolone dampens inflammation and an overactive immune response. This corticosteroid can be used for a variety of inflammatory disorders, with treatment tailored to the severity and type of illness.
Dosage & administration protocols
Medrol treatment schedules require careful tailoring to each patient’s condition and response. Doctors determine methylprednisolone dosage based on diagnosis severity, with UK guidelines recommending precise dosing adjustments to minimise side effects.
Standard treatment regimens
| Condition | Dose | Duration |
|---|---|---|
| Rheumatoid arthritis | 4mg-48mg/day | Long-term maintenance |
| Acute asthma | Up to 32mg/day, tapering | 5-7 days |
| MS relapse | 500mg IV daily | 3-5 days |
| Allergic conditions | Short tapering course | Tapering over 6 days |
Special patient considerations
Liver impairment requires cautious dosing. Renal adjustment isn’t usually needed but kidney function monitoring remains essential. Paediatric dosing follows precise weight calculations, starting at 0.5mg/kg/day split across multiple administrations.
Storage recommendations keep Medrol effective:
- Tablets stored between 15-30°C
- Original packaging protects from moisture
- Away from direct light exposure
- Never freeze oral formulations
Safety profile & contraindications
Medrol carries important UK safety considerations due to potent corticosteroid activity. Understanding medication hazards helps patients make informed treatment choices.
Common side effects
Frequent reactions include sleep disruption, appetite changes and moderate weight gain. Mood alterations can occur, from mild irritability to emotional lability. Skin thinning and bruising susceptibility develops gradually with prolonged treatment.
Serious health risks
Severe reactions demand immediate medical attention:
- Peptic ulcer development
- Significant hyperglycaemia
- Osteoporosis progression
- Adrenal crisis after abrupt discontinuation
Absolute contraindications
Never prescribe during systemic fungal infections due to fatal dissemination risks. Severe hypersensitivity reactions contraindicate future use. Live vaccinations become dangerous during immunosuppression, requiring careful scheduling.
The Medicines and Healthcare products Regulatory Agency mandates warnings about adrenal suppression risks.
Special considerations for long-term users
Prolonged steroid therapy requires comprehensive health protection strategies. Regular NHS monitoring detects complications while preserving treatment benefits.
Essential preventative measures
Bone density protection becomes critical, combining calcium supplements with vitamin D supplementation. Osteoporosis prophylaxis reduces fracture risks substantially. Annual eye examinations detect early glaucoma changes or cataract formation.
Adrenal function monitoring
Chronic suppression of hypothalamic-pituitary-adrenal axis function requires planned tapering. Sudden cessation risks life-threatening adrenal insufficiency. UK guidelines recommend gradual reduction protocols.
Monitoring during long-term treatment may include:
- Regular blood glucose or HbA1c testing
- Bone density (DEXA) scans where indicated
- Regular blood pressure checks
- Regular weight and mood assessments
Alternative steroids comparison
Understanding how Medrol compares to other corticosteroids helps GPs and specialists choose the most appropriate treatment. Each steroid differs in potency, side effect profile and suitability for particular conditions.
| Drug | Potency vs Medrol | UK formulary status |
|---|---|---|
| Prednisolone | 0.8x | 1st-line for most inflammatory conditions |
| Dexamethasone | 5x | Typically specialist use (oncology, cerebral oedema) |
GPs often prefer prednisolone as a first-choice steroid for mild-moderate conditions requiring shorter courses. Dexamethasone’s high potency and long half-life make it useful for specific scenarios but increase risks like adrenal suppression and metabolic side effects. Medrol occupies a middle ground, offering intermediate potency and duration, frequently used for allergy/asthma flare-ups and autoimmune conditions where a moderate-strength steroid is appropriate.
UK availability
Medrol is a prescription-only medicine (POM) and cannot legally be sold over the counter (OTC) without an NHS or private prescription.
Frequently asked questions
Here’s clear, practical advice addressing frequent Medrol queries encountered in UK pharmacies and clinics:
Q: “Is it safe to crush Medrol tablets?”
A: Avoid crushing tablets unless explicitly instructed otherwise by your doctor or pharmacist. If swallowing difficulties exist, they can advise on a suitable alternative.
A: Avoid crushing tablets unless explicitly instructed otherwise by your doctor or pharmacist. If swallowing difficulties exist, they can advise on a suitable alternative.
Q: “Can I drink alcohol while taking Medrol?”
A: Alcohol consumption should be avoided. Combining corticosteroids like Medrol with alcohol significantly increases the risk of stomach irritation and gastric ulceration.
A: Alcohol consumption should be avoided. Combining corticosteroids like Medrol with alcohol significantly increases the risk of stomach irritation and gastric ulceration.
Q: “I forgot my morning dose of Medrol. What should I do?”
A: Take the missed dose as soon as you remember, unless it’s nearly time for your next scheduled dose. Do not double the next dose to compensate for the missed one.
A: Take the missed dose as soon as you remember, unless it’s nearly time for your next scheduled dose. Do not double the next dose to compensate for the missed one.
Q: “Are Medrol steroids safe during pregnancy?”
A: Corticosteroid use in pregnancy requires careful evaluation by a specialist doctor. It’s sometimes used where the benefit outweighs potential risks under close medical supervision but isn’t routine.
A: Corticosteroid use in pregnancy requires careful evaluation by a specialist doctor. It’s sometimes used where the benefit outweighs potential risks under close medical supervision but isn’t routine.
Guidelines for safe & effective use
Maximising the benefit of Medrol while minimising risks hinges on adhering to safe usage principles relevant to UK patients.
The timing of your dose matters:
- Take Medrol tablets in the morning, ideally around breakfast time. This schedule aligns best with the body’s natural cortisol cycle, potentially lowering disruption to sleep patterns.
- Always take tablets with food to reduce the likelihood of stomach irritation or indigestion.
Manage potential interactions:
- Avoid concurrent use of non-steroidal anti-inflammatory drugs (NSAIDs) like ibuprofen without discussing with your doctor/pharmacist, as this combination escalates gastrointestinal bleeding risks.
- Grapefruit juice should be avoided as it interferes with the liver enzymes responsible for breaking down methylprednisolone, potentially leading to higher drug levels.
Safe storage is simple:
- Keep tablets in their original blister strips or bottle, stored out of direct light and moisture at normal room temperature (below 25°C).
- Bathroom cabinets, prone to humidity and temperature changes, are unsuitable storage locations.
A critical safety rule:
- Never abruptly stop taking Medrol if you’ve been on it for more than 3 weeks. Suddenly withdrawing high-dose corticosteroids risks potentially severe adrenal insufficiency. Doses must always be carefully tapered down under medical oversight.
Always consult the detailed MHRA-approved Patient Information Leaflet (PIL) included in every pack for batch-specific information and comprehensive warnings.